
CPT 31622: diagnostic bronchoscopy and the endoscopy base code
31622 is a diagnostic bronchoscopy, billed alone only when nothing more than the look and the washings was done. In the CMS file it is also the base code that 21 other entries name, which changes how it is paid beside them.
 Written by Salman Saeed, CEO and Co-Founder · Reviewed by a Certified Medical Coder · Last reviewed October 2026
In short: 31622 is billed alone for a diagnostic bronchoscopy. Surgical bronchoscopy codes name it as their base, and CMS does not pay the base separately when it is reported with one. The practitioner MUE is 1 per date and the global period is 000.
What does CPT 31622 report?
31622 reports a diagnostic bronchoscopy: a scope passed into the airways to look and to collect washings, with no further step that has a code of its own. CMS's short label is "Dx bronchoscope/wash." It is also the code the fee schedule uses as the starting point for the bronchoscopy family.
| Item | Value in the file |
|---|---|
| Payment status | A (active code) |
| Work RVU | 2.47 |
| Total RVU, non-facility / facility | 8.45 / 3.60 |
| Global period | 000 |
| Multiple procedure indicator | 2 |
| NCCI MUE, practitioner table Q4 2026 | 1 per date, indicator 3 |
Why is 31622 called the base code of its family?
The fee schedule file has an endoscopic base field. For 21 entries it holds 31622, among them 18 CPT codes and three Category III codes. CMS gives those entries multiple procedure indicator 3, the special rule for a family of endoscopies.
| Code | CMS file label | Work RVU |
|---|---|---|
| 31623 | Dx bronchoscope/brush | 2.56 |
| 31624 | Dx bronchoscope/lavage | 2.56 |
| 31625 | Bronchoscopy w/biopsy(s) | 3.03 |
| 31628 | Bronchoscopy/lung bx each | 3.46 |
| 31629 | Bronchoscopy/needle bx each | 3.66 |
| 31635 | Bronchoscopy w/fb removal | 3.33 |
| 31645 | Brnchsc w/ther aspir 1st | 2.81 |
CMS says that when an endoscopy is reported with its own base, the base is not paid separately, because its payment is inside the other endoscopy. Multiple endoscopy rules are applied within the family first, and only then is the family ranked against other procedures that day. A few bronchoscopy codes sit outside the family: 31615, 31646, 31652 and 31653 name no base.
When is 31622 billed alone, and when does another code replace it?
Alone only when nothing more than the look and the washings was done. NCCI Chapter V, section C, sets the limits:
- A diagnostic endoscopy is not separately reportable with a surgical endoscopy. In NCCI's foreign body example only 31635 is reported, not 31622 as well (item 3).
- If that attempt fails and the surgeon opens the chest, the diagnostic bronchoscopy may be reported with the open procedure, and modifier 58 can show the two were staged (item 3).
- A look at the nose, throat and larynx during a fiberoptic bronchoscopy is included. A separate laryngoscopy counts only when a second scope was needed for a second region (item 3).
- Report the most comprehensive code for the work done, with modifier 51 on secondary codes when more than one is needed (item 6).
- Fluoroscopy during bronchoscopy is integral (Chapter V, item 16).
How do office and hospital settings change what 31622 pays?
Quite a lot. The file shows 8.45 total RVUs in the non-facility column and 3.60 in the facility column. Chapter 12, section 20.4.2, says the place of service on the claim decides which rate applies, and that for a registered inpatient (POS 21) or a hospital outpatient (POS 19 or 22) the facility rate is paid wherever the visit took place.
Some payers ask for prior authorization when the site is an outpatient hospital. The list is on pulmonology billing.
How does 31622 appear on the claim?
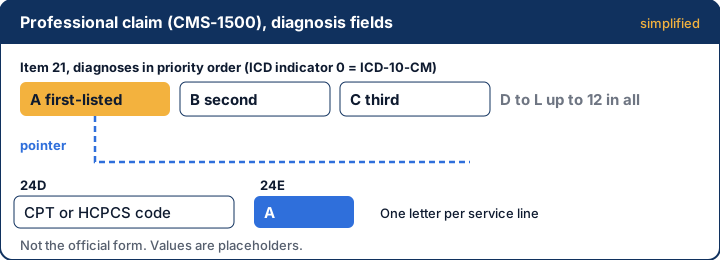
On the CMS-1500, 31622 goes in Item 24D with 1 in Item 24G and the POS in Item 24B. The practitioner MUE of 1 carries indicator 3, a clinical date of service edit, so a second bronchoscopy on the date needs its own support.
Where does 31622 go, and how do family codes follow?
A diagnostic bronchoscopy is one line, 31622 in Item 24D with 1 unit in Item 24G. If a biopsy or other family code is added, it replaces the base code rather than sitting beside it, so only one bronchoscopy code in the family is on the claim for the session. Item 24E points to the lung finding or symptom.
On a hospital outpatient bill, the revenue code is in FL 42, 31622 in FL 44, the date in FL 45 and 1 unit in FL 46.

RVU26D gives 31622 status A and a 000 global, and the MUE table allows 1 per date with indicator 3.
Example: A patient with a lung nodule has a washing-only bronchoscopy on 10/19. The line is 31622, pointer A (R91.1), 1 unit, $480.00. If a biopsy is also done, the family code for it is billed alone and 31622 is not added.
Why does a 31622 line deny?
| Code | What X12 says | What usually causes it on 31622 |
|---|---|---|
| CARC 59 | Processed based on multiple or concurrent procedure rules | 31622 reduced beside another bronchoscopy |
| CARC 97 | The benefit for this service is included in the payment/allowance for another service/procedure that has already been adjudicated | Billed with a biopsy or therapeutic code from its family |
| CARC 197 | Precertification/authorization/notification/pre-treatment absent | Outpatient hospital site without an approval |
| CARC 151 | The information submitted does not support this many/frequency of services | Two units on one date |
If these denials keep coming back, our denial management team can work them. Related reading: CPT 94010, CPT 94002 and medical coding.
Related codes
- Physician Fee Schedule relative value files, RVU26D (October 2026) · CMS
- Medicare NCCI Medically Unlikely Edits, practitioner services table, effective 10-01-2026 · CMS
- 2026 NCCI Medicare Policy Manual, Chapter V: Surgery: Respiratory, Cardiovascular, Hemic and Lymphatic Systems · CMS
- Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners · CMS
- Medicare Claims Processing Manual, Chapter 26: Completing and Processing Form CMS-1500 Data Set · CMS
- Claim Adjustment Reason Codes · X12
- Medicare Claims Processing Manual, Chapter 25: Completing and Processing the Form CMS-1450 Data Set · CMS
We check every rule, code and deadline against the official source. See our editorial policy.
Common questions
Straight answers from the team that does the work.
Ask a billing lead directly. A 20-minute call, Monday to Friday, 9am to 5pm Eastern.
01How do I bill bronchoscopy with biopsy?
Report the code that describes the biopsy, such as 31625, and leave 31622 off. The biopsy codes name 31622 as their base in the CMS file, so the base is not paid separately with them, and NCCI says a diagnostic endoscopy is not reported with a surgical one.
02Can 31622 be billed with foreign body removal 31635?
No. NCCI Chapter V gives this exact case as its example: when the scope finds a foreign body and the attempt to remove it is made during the same bronchoscopy, only the surgical code 31635 is reported, not 31622 as well.
03Can I bill a laryngoscopy with a bronchoscopy?
Not for the routine look. NCCI Chapter V says a fiberoptic bronchoscopy includes examining the nasal cavity, pharynx and larynx. A separate laryngoscopy is reportable only when two regions each needed a medically necessary procedure with different types of scope.
04What does endoscopic base code mean on the fee schedule?
It is a field in the CMS relative value file that names the simplest scope procedure in a family. For bronchoscopy it is 31622. If a family member is billed with its base, CMS does not pay the base separately, and the multiple endoscopy rules apply within the family first.
05How many units of 31622 can be billed per date?
One. The practitioner MUE table effective October 1, 2026 lists 31622 at 1 with indicator 3, a clinical date of service edit. A second unit would need a separate documented bronchoscopy, such as a second session, and the note should show why it was needed.



Bronchoscopy lines reduced or denied?
We check the family rules before a base code goes out with a biopsy code.