
CPT 99213: established patient office visit, low decision making
99213 reports an office or other outpatient visit for an established patient when the medical decision making is low, or when the practitioner's total time on the date reaches 20 minutes. It is the most common level in primary care, and the highest one a resident can have billed under the Medicare primary care exception.
 Written by Salman Saeed, CEO and Co-Founder · Reviewed by a Certified Medical Coder · Last reviewed October 2026
In short: 99213 is the low-level established office visit, chosen by low decision making or 20 minutes of total time. Its own wrinkle is the primary care exception: CMS still allows teaching physicians to bill 99213 for a resident's visit, but no longer 99214 or 99215.
What does CPT 99213 report?
99213 is an E/M code for an established patient seen in an office or other outpatient setting. Low MDM or time sets the level. CMS labels it "Office o/p est low 20 min" in its fee schedule file.
| Item | Value in the file |
|---|---|
| Payment status | A (active code) |
| Work RVU | 1.30 |
| Non-facility total RVU | 2.85 |
| Facility total RVU | 1.72 |
| Global period | XXX |
| MUE value and indicator | 2, with indicator 3 (date of service edit, clinical data) |
In the same file 99212 carries a 10 minute label and 99214 a 30 minute label.
How do you support 99213: by MDM or by time?
Chapter 12 of the Medicare Claims Processing Manual says that since January 1, 2023, practitioners choose the office visit level by MDM or by the time they spend, and history and exam no longer affect the level.
- By MDM: the note shows a low level under the AMA E/M guidelines. MLN006764 sends practitioners to those guidelines for the elements of MDM.
- By time: record total minutes on the date, or a start and stop time. The CY 2025 final rule restates the 99213 threshold as 20 minutes met or exceeded, and Chapter 12 says the CPT midpoint rule does not apply, so 19 minutes does not support 99213.
- Chapter 12 states that billing a higher level when a lower one is warranted is not medically necessary.
A physician spends 6 minutes on labs, 12 with the patient and 5 charting on one date. The 23 minutes support 99213 and fall short of the 30 minute label on 99214.
Can you bill 99213 twice on one day, or with a procedure?
Not for the same problem. Chapter 12, section 30.6.7 B, says the MAC may not pay two office visits by the same physician, or physicians of the same specialty in one group, for one patient on one day unless the note shows the visits were for unrelated problems that could not be handled in the same encounter.
With a procedure or vaccine, 99213 can stand beside the other service when the visit is significant and separately identifiable. The NCCI Policy Manual, Chapter XI, says 99212 to 99215 are separately reportable with modifier 25 on drug or vaccine administration days. 99211 is the exception. See modifier 25.
What is the primary care exception, and why does it matter for 99213?
Under the Medicare primary care exception, teaching physicians bill a resident's lower-level visits without being present for the key portion. CMS says they attach the GE modifier to 99202 and 99203 and to 99211 through 99213. The pandemic-era extension to 99214 and 99215 has ended.
MLN006764 says only MDM can set the level under the exception, so a 99213 billed this way needs the GE modifier and documented low MDM, not a minute count.
Can you add G2211 to 99213?
Yes, when the relationship supports it. 99213 is one of the base codes for G2211, the visit complexity add-on, which MLN006764 says can be reported with 99202 to 99205 and 99211 to 99215. The relationship, not the level, decides, so a low-level visit can qualify.
How does 99213 appear on the claim?
On the CMS-1500, 99213 goes in Item 24D with 1 unit in Item 24G and the place of service in Item 24B. The NCCI practitioner MUE table effective October 1, 2026 lists 99213 at 2 with adjudication indicator 3, a date of service edit based on clinical data. The same-day rule in section 30.6.7 B still applies.
Prolonged service add-on G2212 is not an option here. Chapter 12 ties G2212 to 99205 and 99215, so a long 99213 visit is billed at the higher level its time supports.
Which claim fields must agree on a 99213 line?
A 99213 line is only as good as the three fields beside it. Item 24D holds the code and any modifier, Item 24E holds the pointer letter that links the line to a diagnosis in Item 21, and Item 24G holds the units. Chapter 26 says to enter only one reference letter per line, so point to the diagnosis that drove the visit, not simply the first one listed.
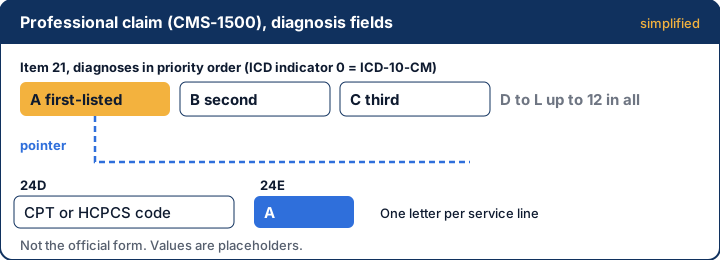
RVU26D gives 99213 status A and a global period of XXX, and the practitioner MUE table caps it at 2 units a day. Units stay at 1 because the code describes one visit. A second visit on the same date needs its own support in the chart.
Example: Dr. Reyes sees an established patient on 10/14 for a diabetes recheck and a blood pressure check. Item 21 reads A E11.9 and B I10. The visit line shows 99213, pointer A, 1 unit and a $118.00 charge. If the pointer were blank, the payer would return the claim as incomplete under CO-16; if it pointed to a diagnosis that does not fit the visit, CO-11 is the likelier result.
Why is 99213 denied or downcoded?
| Code | What X12 says | What usually causes it |
|---|---|---|
| CO-4 | The procedure code is inconsistent with the modifier used | Modifier 25 or GE on the wrong line, or missing where a procedure is billed |
| OA-18 | Exact duplicate claim or service | A second 99213 on one date from the same group |
| CO-97 | The benefit is included in the payment for another service already adjudicated | A same-day visit folded into a procedure or another visit |
| CO-150 | The information submitted does not support this level of service | A note with no MDM or time that reaches low |
If these denials keep coming back, our denial management team can work them. For the level above, see 99214, and for the specialty view see urgent care billing, internal medicine billing and family medicine billing.
Related codes
- Physician Fee Schedule relative value files, RVU26D (October 2026) · CMS
- Medicare NCCI Medically Unlikely Edits, practitioner services table, effective 10-01-2026 · CMS
- Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners · CMS
- Evaluation and Management Services (MLN006764, May 2026) · CMS
- 2026 NCCI Medicare Policy Manual, Chapter XI: Medicine and Evaluation and Management Services · CMS
- CY 2025 Physician Fee Schedule final rule (89 FR 97710) · Federal Register
- FAQs about the E/M visit complexity add-on HCPCS code G2211 · CMS
- Claim Adjustment Reason Codes · X12
- Medicare Claims Processing Manual, Chapter 26: Completing and Processing Form CMS-1500 Data Set · CMS
We check every rule, code and deadline against the official source. See our editorial policy.
Common questions
Straight answers from the team that does the work.
Ask a billing lead directly. A 20-minute call, Monday to Friday, 9am to 5pm Eastern.
01How do I choose between 99213 and 99214?
Use whichever of MDM or total time supports the higher code. 99213 needs low MDM or 20 minutes; 99214 needs moderate MDM or 30 minutes. Chapter 12 says time must be fully met, so 29 minutes stays 99213 unless the MDM is moderate.
02How many minutes does 99213 require?
Twenty minutes of total practitioner time on the date of the visit, met or exceeded. CMS says the CPT midpoint rule does not apply, so 19 minutes does not qualify. Record total minutes or a start and stop time in the note.
03Is 99213 still covered under the primary care exception?
Yes. CMS says teaching physicians bill 99202, 99203 and 99211 through 99213 under the exception with the GE modifier. The temporary pandemic policy that added 99214 and 99215 has ended. The level must rest on MDM, since time cannot be used under the exception.
04Can I bill 99213 with a vaccine or injection on the same day?
Yes, if the visit is significant and separately identifiable from the vaccine or drug administration. The NCCI Policy Manual says 99212 to 99215 may carry modifier 25 in that case. 99211 cannot be billed with those services, so a nurse-only visit does not qualify.
05What is the NCCI MUE for 99213?
The practitioner MUE table effective October 1, 2026 lists 99213 at 2 units per date of service, adjudication indicator 3. It does not override the Medicare same-day rule, which needs unrelated problems documented before a group is paid for two visits.
06Can G2211 be billed with 99213?
Yes. CMS lists 99211 to 99215 as base codes for G2211. Whether the add-on is right depends on the practitioner being the continuing focal point for the patient's care, or giving ongoing care for a serious or complex condition. A one-off minor problem does not qualify.


Visit levels paid one step low?
We code from the chart and check the time or MDM behind every established visit before it is billed.