
CPT 95251: CGM analysis, interpretation and report
CPT 95251 is the code for the practitioner's analysis, interpretation and report of continuous glucose monitor data. It is a professional-component-only code with an XXX global and a daily limit of one.
 Written by Salman Saeed, CEO and Co-Founder · Reviewed by a Certified Medical Coder · Last reviewed October 2026
In short: 95251 carries 0.68 work RVUs in the October 2026 CMS file, no modifier 26 or TC, and an MUE of 1 per date of service. A same-day visit needs modifier 25 and its own work, which can also cost a Medicare practice the G2211 add-on.
What does CPT 95251 report?
CPT 95251 reports the practitioner's analysis, interpretation and written report of data recorded by a continuous glucose monitor (CGM). The CMS fee schedule file labels it "Cont gluc mntr analysis i&r". It pays for the reading, not for sensor setup and not for supplies.
It is one of three CGM codes. In the same CMS file, 95249 and 95250 cover setup and teaching, carry no physician work value and are technical-component-only codes. 95251 is the one with physician work.
| Item | Value |
|---|---|
| Payment status | A (active code) |
| Work RVU | 0.68 |
| Practice expense RVU, non-facility and facility | 0.32 and 0.32 |
| Malpractice RVU | 0.05 |
| Total RVU, non-facility and facility | 1.05 and 1.05 |
| PC/TC indicator | 2, professional component only |
| Global period | XXX, the global concept does not apply |
| NCCI MUE, practitioner table, October 1, 2026 | 1 (indicator 2, policy edit; rationale: code descriptor) |
These are relative value units, not dollars. The facility and non-facility totals are equal, so the place of service does not change the value.
Does 95251 need modifier 26?
No. The RVU26D file defines PC/TC indicator 2 as a professional-component-only code and says modifiers 26 and TC cannot be used with these codes. 95251 is already the physician's share, so it goes on the claim bare.
The setup codes 95249 and 95250 carry indicator 3, technical component only. The reading and the setup are different claims with different values.
How often can 95251 be billed?
The CMS MUE for 95251 is 1 unit per date of service, adjudication indicator 2, a policy-based date of service edit. The rationale column reads "Code Descriptor / CPT Instruction", so the limit comes from how the code is defined, not from a Medicare payment rule.
RVU26D states no calendar limit for the code. Any monthly ceiling is a CPT instruction or a payer policy. For commercial plans, read the plan's policy on CGM interpretation before sending a second reading in the same month. Medicare Advantage plans follow their own policy documents.
The code describes a written report, so keep the analysis in the chart with the date it was done and the recording it covers.
Can 95251 be billed with an office visit?
Yes, when the visit stands on its own work. Chapter I of the NCCI Policy Manual says XXX procedures fall outside the global surgery rules, and that an E/M service may be reported with modifier 25 if it is significant and separately identifiable. The visit cannot include work inherent in the procedure or time for interpreting its result.
A patient with type 2 diabetes returns for a scheduled visit. The practitioner reads the monitor report, then changes a medication and orders labs.
One more trap for Medicare practices. G2211 is not paid when the base visit carries modifier 25, except on days with a wellness visit, vaccine administration or a Part B preventive service. A same-day 95251 therefore usually costs the add-on.
How does 95251 sit on the claim?
- CMS-1500 box 24D: 95251 with no modifier 26 or TC, one unit.
- Box 24B place of service: the RVUs are the same in an office and in a facility.
- Billing provider: the practitioner who interpreted the study. Sensors and receivers supplied to the patient bill separately through the DME channel, covered on our endocrinology billing page.
Which fields hold the glucose monitor read?
The monitoring analysis is one line, 95251 in Item 24D with 1 unit in Item 24G and a pointer in Item 24E to the diabetes diagnosis.
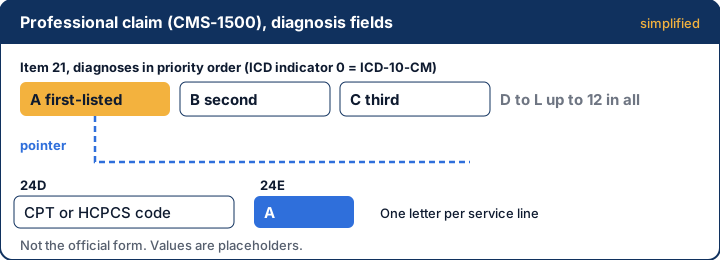
RVU26D gives 95251 status A and global XXX, and the MUE table allows 1 per date with indicator 2, a policy edit.
Example: A patient wears a sensor for 14 days and the clinic interprets the report on 10/19. The line is 95251, pointer A (E11.65), 1 unit, $42.00. A second 95251 on the same date draws CO-151 against the MUE of 1.
Why do 95251 claims deny?
| Code | What X12 says | What usually causes it on 95251 |
|---|---|---|
| CO-151 | Payment adjusted because the information submitted does not support this many or this frequency of services | A second reading in the same month, or two units on one date. |
| CO-97 | The benefit is included in the payment for another service already adjudicated | The same-day visit went out without modifier 25. |
| CO-50 | Non-covered because the payer does not deem it medically necessary | The payer's policy does not cover this patient or diagnosis. |
| CO-16 | Claim lacks information or has a billing error | No report date, or the study is missing from the chart on request. |
If these denials keep coming back, our denial management team can work them.
Related codes
- Physician Fee Schedule relative value files, RVU26D (October 2026) · CMS
- Medicare NCCI Medically Unlikely Edits, practitioner services table, effective 10-01-2026 · CMS
- NCCI Policy Manual for Medicare Services, 2026, Chapter I · CMS
- CY 2025 Physician Fee Schedule final rule (89 FR 97710) · Federal Register
- Claim Adjustment Reason Codes · X12
- Medicare Claims Processing Manual, Chapter 26: Completing and Processing Form CMS-1500 Data Set · CMS
We check every rule, code and deadline against the official source. See our editorial policy.
Common questions
Straight answers from the team that does the work.
Ask a billing lead directly. A 20-minute call, Monday to Friday, 9am to 5pm Eastern.
01How do I bill CGM interpretation 95251?
Bill 95251 once for each completed analysis, interpretation and written report, under the practitioner who did the reading, with no modifier 26 or TC. Add modifier 25 to a same-day visit only when it has separate work. Sensor setup is a different code and a different payer rule.
02Can 95251 be billed more than once in a month?
The CMS limit is 1 unit per date of service. Anything stricter comes from the CPT book or the payer. RVU26D shows no monthly limit. Check the plan's policy before billing a second reading in the same month, and keep each report dated.
03Is 95251 payable in a facility?
Yes. RVU26D lists 95251 with a total of 1.05 relative value units in both the facility and non-facility columns, so place of service does not change its value. The practitioner's professional claim still goes out on the CMS-1500, not the facility claim.
04What is the difference between 95249, 95250 and 95251?
95249 and 95250 are the setup and teaching codes. In RVU26D both are technical-component-only, with no work value, so they pay for equipment and staff time. 95251 is the interpretation, with 0.68 work RVUs, billed by the practitioner who reads the data and writes the report.
05Does 95251 count toward a visit's complexity?
No. The NCCI manual says a separate E/M visit cannot include time for interpreting the result of an XXX procedure. Level the visit on its own decisions, such as dose changes and lab orders, and bill 95251 on its own line.


CGM readings denied as duplicates?
We check the date, the report and the modifier 25 split before the reading is billed.