
CPT 93458: left heart catheterization with coronary angiography and ventriculography
93458 reports a left heart catheterization that includes imaging of the coronary arteries and of the left ventricle in the same session. It has a 000-day global and PC/TC indicator 1, so the cardiologist in a hospital cath lab bills it with modifier 26 while the hospital reports the technical work.
 Written by Salman Saeed, CEO and Co-Founder · Reviewed by a Certified Medical Coder · Last reviewed October 2026
In short: 93458 is the combined left heart cath with coronary angiography and ventriculography. Medicare allows one unit a day (MAI 3), the cath lab physician adds 26, and catheter placement, fluoroscopy, injections and ECG strips are included in the code.
What does CPT 93458 report?
CPT 93458 reports a left heart catheterization with coronary angiography and left ventriculography, meaning dye imaging of the coronary arteries and of the left pumping chamber. CMS prints its label as "L hrt artery/ventricle angio".
| Item | Value in RVU26D (October 2026) and the Q4 2026 MUE files |
|---|---|
| Payment status | A (active; paid separately under the fee schedule if covered) |
| PC/TC indicator | 1 (26 and TC allowed) |
| Global period | 000 (the day of the procedure only) |
| Multiple procedure indicator | 2 (standard reduction when other indicator 1, 2 or 3 procedures are billed the same day) |
| Work RVU and totals | 5.46 work; 30.24 whole, 8.60 with 26, 21.64 with TC |
| Facility setting | NA flag on the whole and TC rows; none on the 26 row |
| NCCI MUE | 1 per date of service, indicator 3, practitioner and outpatient hospital |
How do I bill left heart catheterization with imaging?
Pick the one code that matches what was imaged, and bill it once. The coronary angiography code 93454 and the ventriculography code 93452 are the narrower parts of 93458, and reporting them together repeats work the combined code describes, and chapter I section H of the NCCI Policy Manual says redundant codes are not reported together.
| Code | CMS label | Work RVU |
|---|---|---|
| 93452 | Left hrt cath w/ventrclgrphy | 4.39 |
| 93454 | Coronary artery angio s&i | 4.43 |
| 93455 | Coronary art/grft angio s&i | 5.16 |
| 93458 | L hrt artery/ventricle angio | 5.46 |
| 93459 | L hrt art/grft angio | 6.19 |
| 93460 | R&l hrt art/ventricle angio | 6.92 |
In a hospital cath lab the cardiologist bills 93458 with 26 and the POS of the hospital: 22 or 19 outpatient, 21 inpatient. The hospital reports the technical work on its UB-04 in FL 44, with units in FL 46.
What is included in 93458, and what can be added?
| Item | NCCI Policy Manual, chapter XI section I |
|---|---|
| Catheter or needle placement, infusion, fluoroscopy, ECG rhythm strips, ultrasound guidance | Included in a cath; not reported separately (item 15) |
| Cardiac output measurement, 93598 | Not reported with 93451 to 93461 (item 5) |
| Diagnostic ECG before or after the procedure | May be reported with 59 or XU (item 16) |
| Iliac or femoral angiography at withdrawal | HCPCS G0278 when necessary; aortography 75625 or 75630 only for a complete study (item 18) |
| Closure device at the access site | G0269, with no imaging code (item 19) |
| Transseptal puncture | Add-on 93462, global ZZZ, MUE 1; not with a transseptal approach to 93590 (item 32) |
How does a cath combine with a PCI, a visit or a return to the lab?
When diagnostic coronary angiography is medically necessary and comes before a stent or angioplasty, item 17 allows the catheterization and dye injections to be reported separately from the PCI. The PCI code itself includes its own catheter work, so the pair needs the right modifier; see CPT 92928.
A visit on the day of a 000-day procedure is part of the procedure. Chapter I section D treats the decision to perform it as included, and only a significant, separately identifiable service takes modifier 25. Chapter 12 section 40.1 counts a cardiac catheterization suite as an operating room, so a return trip for a complication is reported with modifier 78.
Where do 93458 and its modifiers sit on the form?
The cath lab physician's line carries 93458 in Item 24D, usually with 26, and 1 unit in Item 24G. Item 24E points to the heart condition that prompted the study, such as angina or an abnormal stress test. Chapter 26 sets one pointer letter per line, so the supporting diagnoses stay in Item 21 for the record.
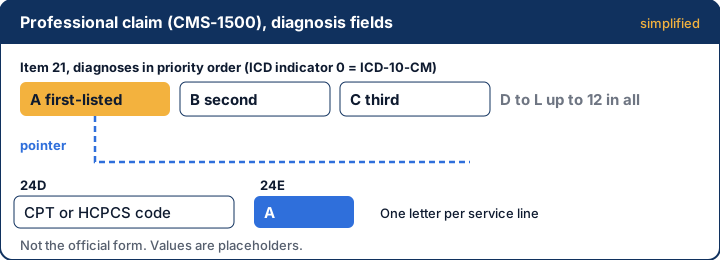
On the hospital claim, the cath lab revenue code goes in FL 42, 93458 in FL 44, the procedure date in FL 45 and units in FL 46. Included work such as dye injection and fluoroscopy has no line of its own.

RVU26D lists 93458 as status A with a global period of 000, and the MUE table allows 1 per date with indicator 3.
Example: A patient with unstable angina has a combined left heart cath on 10/08. The physician line is 93458 with 26, pointer A (I20.0), 1 unit, $690.00. The hospital claim for the same date shows the code once in FL 44 with 1 in FL 46.
Why do 93458 claims deny?
| CARC | What X12 says | What usually causes it on a cath |
|---|---|---|
| 97 | The benefit is included in the payment for another service already adjudicated | Fluoroscopy, injection, cardiac output or 93454 billed with 93458 |
| 4 | The procedure code is inconsistent with the modifier used | 26 missing for the professional line or left on a facility claim |
| 59 | Processed based on multiple or concurrent procedure rules | Second procedure the same day, such as a PCI |
| 151 | Information submitted does not support this many or this frequency of services | Two units of 93458 on one date |
| 50 | Non-covered because not deemed a medical necessity by the payer | Elective cath without the payer's required indication |
If these denials keep coming back, our denial management team can work them. Authorization for elective caths is covered under prior authorization.
Related codes
- Physician Fee Schedule relative value files, RVU26D (October 2026) · CMS
- Medicare NCCI Medically Unlikely Edits, practitioner and outpatient hospital tables effective 10-01-2026 · CMS
- NCCI Policy Manual for Medicare Services, 2026 (chapters I, V and XI) · CMS
- Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners · CMS
- Medicare Claims Processing Manual, Chapter 25: Completing and Processing the Form CMS-1450 Data Set · CMS
- Medicare Claims Processing Manual, Chapter 26: Completing and Processing Form CMS-1500 Data Set · CMS
- Claim Adjustment Reason Codes · X12
We check every rule, code and deadline against the official source. See our editorial policy.
Common questions
Straight answers from the team that does the work.
Ask a billing lead directly. A 20-minute call, Monday to Friday, 9am to 5pm Eastern.
01How do I bill left heart catheterization with imaging?
Report the single code that matches the imaging done: 93458 for coronary angiography plus ventriculography, 93452 for ventriculography alone, 93454 for coronary angiography alone. In a hospital cath lab the physician adds modifier 26, and the hospital reports the technical work.
02Can I bill 93458 with fluoroscopy or an ECG?
No for fluoroscopy and ECG rhythm strips, which NCCI chapter XI says are included in a cath. A diagnostic ECG performed before or after the procedure may be reported separately with modifier 59 or XU, but chest-pain strips taken during it may not.
03Can a diagnostic cath be billed in the same session as a stent?
Yes when the angiography was medically necessary and came first, per NCCI chapter XI item 17. The PCI code includes its own catheterization, so the diagnostic cath must be the separate, necessary study. Check the modifier indicator in the procedure-to-procedure table.
04What is the global period for 93458?
000 days. RVU26D gives it the day of the procedure only. A visit that day is included unless it is a significant, separately identifiable service with modifier 25. Care for a complication that needs a return to the cath lab uses modifier 78, since the lab counts as an operating room.
05How many units of 93458 can be billed per day?
One. The Q4 2026 MUE files show 1 for practitioners and outpatient hospitals, with indicator 3 and the rationale nature of service. A second unit would need a record of a distinct, medically necessary second study, and a contractor may then bypass the edit.



Cath lab claims splitting between 26 and the facility?
We check the modifier, place of service and included services on each cath before it is sent.