
CPT 49505: initial inguinal hernia repair, reducible
49505 reports an open first-time repair of an inguinal hernia that can be pushed back, in a patient past early childhood. It carries a 090-day global, mesh is part of the code, and a repair on both sides is one line with modifier 50. The January 2023 deletions that NCCI lists did not remove it.
 Written by Salman Saeed, CEO and Co-Founder · Reviewed by a Certified Medical Coder · Last reviewed October 2026
In short: 49505 is the open, initial, reducible inguinal repair for patients older than 5 by CMS's label. It has a 090 global, a MUE of 1, a 150 percent bilateral rule, and assistant and co-surgeon payment. The abdominal wall repair codes sit in a separate family with a 000 global and no bilateral rule.
What does CPT 49505 report?
CPT 49505 reports an open repair of the first inguinal hernia on a side, one that can be reduced, in a patient past early childhood. CMS prints its label as "Prp i/hern init reduc >5 yr"; the age wording in full sits in the CPT codebook. A trapped hernia that cannot be reduced is 49507.
| Item | Value in RVU26D (October 2026) and the Q4 2026 MUE file |
|---|---|
| Payment status | A (active; paid separately under the fee schedule if covered) |
| Global period | 090, split 9% pre-operative, 81% intra-operative, 10% post-operative |
| Multiple procedure and bilateral | Multiple procedure 2 (standard reduction); bilateral 1 (150 percent) |
| Assistant, co-surgeon, team | Assistant 2 (may be paid); co-surgeon 1 (documentation required); team 0 |
| Work RVU and total | 7.76 work; 15.21 total in the facility setting; non-facility is NA |
| NCCI MUE | 1 per date, MAI 2, basis CMS policy, practitioner and outpatient hospital |
Which hernia code applies: inguinal, laparoscopic or abdominal wall?
Inguinal and abdominal wall repairs are separate families. The abdominal wall repair codes that NCCI names (49591 to 49596, 49613 to 49618, 49621 to 49623) sit at a 000 global with bilateral indicator 0.
| Code | CMS short label | Work RVU | Global | Bilateral |
|---|---|---|---|---|
| 49505 | Prp i/hern init reduc >5 yr | 7.76 | 090 | 1 |
| 49507 | Prp i/hern init block >5 yr | 8.86 | 090 | 1 |
| 49520 | Rerepair ing hernia reduce | 9.74 | 090 | 1 |
| 49650 | Lap ing hernia repair init | 6.20 | 090 | 1 |
| 49591 | Rpr aa hrn 1st < 3 cm rdc | 5.81 | 000 | 0 |
| 49613 | Rpr aa hrn rcr < 3 rdc | 7.23 | 000 | 0 |
NCCI Policy Manual chapter VI says CPT codes 49560, 49566, 49652 and 49657 and the mesh add-on 49568 were deleted on January 1, 2023, and RVU26D has no rows for them.
Is mesh billed separately, and what else is bundled?
Mesh is not billed separately: NCCI chapter VI, section E, item 7, says most codes for a procedure that includes a hernia repair include insertion of mesh or other prosthesis, so a mesh implantation code such as 15777 is not reported unless the CPT codebook says so for that procedure.
- A repair at the incision site of another abdominal operation is not separately reportable (item 4), and neither is an incidental repair.
- A necessary repair at a different site is separately reportable.
- A panniculectomy at the incision site of a hernia procedure is not reported with 15830 (item 8).
- A laparoscopic repair converted to open is reported as the open code only.
How do I report a repair on both sides?
Report 49505 once with modifier 50 and 1 unit. Chapter 12 section 40.7 says a procedure not described as bilateral is reported on a single line with 50, and the bilateral indicator of 1 pays up to 150 percent of the single-code amount. Chapter I of the NCCI manual says the MUE of 1 for a bilateral indicator of 1 follows the same one-unit rule.
The manual adds a note that this differs from the CPT coding guidelines, which bill bilateral procedures as two line items, so read each commercial payer policy before you copy the Medicare habit.
Which visits and complications fall in the 090-day global?
The decision visit is paid with modifier 57; related follow-up for 90 days and complications that need no return to the operating room are not (chapter 12 section 40.1). A return for a related problem uses 78, a planned, staged repair uses 58, and an unrelated operation uses 79.
An assistant is paid 16 percent (indicator 2, section 20.4.3). Co-surgeons need documented medical necessity and are paid 62.5 percent each (section 40.8).
How does 49505 appear on the claim?
On the CMS-1500, Item 24B holds place of service 22 or 24, Item 24D holds 49505 with 50 where it applies, and Item 24G holds 1. The MUE is an absolute indicator 2 edit, so a second unit instead of modifier 50 cannot be fixed on appeal. A hospital outpatient UB-04 puts the code in FL 44.
Where do the hernia code, side and mesh go?
An open inguinal hernia repair is one line with 49505 in Item 24D, 1 unit in Item 24G and the side modifier when both sides are done. RVU26D sets the bilateral indicator to 1, so the 150% adjustment applies if the code is reported for both sides. Item 24E points to the hernia diagnosis.
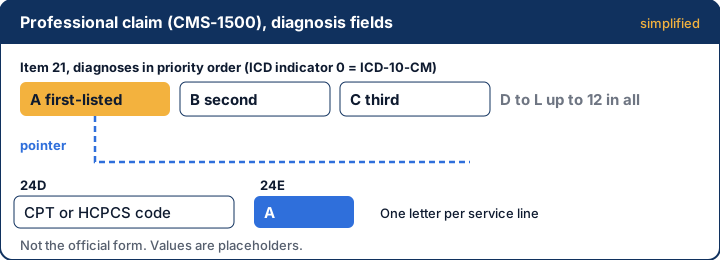
On the hospital outpatient bill, the operating room revenue code is in FL 42, 49505 in FL 44, the date in FL 45 and units in FL 46. The file shows a 090 global with assistant indicator 2. The MUE table allows 1 per date with indicator 2.

Example: A patient has a right inguinal hernia repaired on 10/14. The line is 49505 RT, pointer A (K40.90), 1 unit, $1,700.00. For both sides, report 49505 on two lines with RT and LT or with 50 as the payer prefers.
Why do 49505 claims deny?
| CARC | What X12 says | What usually triggers it on a hernia claim |
|---|---|---|
| 97 | The benefit for this service is included in the payment/allowance for another service/procedure that has already been adjudicated | Mesh code or a second repair at the incision site |
| 151 | Payment adjusted because the payer deems the information submitted does not support this many/frequency of services | 49505 with 2 units or on two lines for the two sides |
| 4 | The procedure code is inconsistent with the modifier used | 50 on an abdominal wall repair code, which has bilateral indicator 0 |
| 59 | Processed based on multiple or concurrent procedure rules | Reduction applied after a second repair on the same date |
If these denials keep coming back, our denial management team can work them.
Related codes
- Physician Fee Schedule relative value files, RVU26D (October 2026) · CMS
- Medicare NCCI Medically Unlikely Edits, practitioner and outpatient hospital tables effective 10-01-2026 · CMS
- NCCI Policy Manual for Medicare Services, 2026 · CMS
- Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners · CMS
- Medicare Claims Processing Manual, Chapter 26: Completing and Processing Form CMS-1500 Data Set · CMS
- Medicare Claims Processing Manual, Chapter 25: Completing and Processing the Form CMS-1450 Data Set · CMS
- Claim Adjustment Reason Codes · X12
We check every rule, code and deadline against the official source. See our editorial policy.
Common questions
Straight answers from the team that does the work.
Ask a billing lead directly. A 20-minute call, Monday to Friday, 9am to 5pm Eastern.
01How do I bill an inguinal hernia repair?
Report 49505 once for an open first-time repair that is reducible, 49507 if it is trapped, and 49520 or 49521 if it is a recurrence. Laparoscopic repairs use 49650 or 49651. Mesh is part of the code. A repair on both sides goes on one line with modifier 50.
02Do the 2023 hernia code changes affect 49505?
No. NCCI lists 49560, 49566, 49652, 49657 and the mesh add-on 49568 as deleted on January 1, 2023, and 49505 is not among them. It stays active in RVU26D. The abdominal wall repair codes NCCI names, such as 49591, have a 000 global and bilateral indicator 0.
03Can I bill mesh with 49505?
No. NCCI Policy Manual chapter VI, section E, item 7, says most codes for a procedure that includes a hernia repair include the insertion of mesh or other prosthesis. A mesh implantation code is reported only when the CPT codebook says it can be reported with that procedure.
04How do I report a bilateral inguinal hernia repair to Medicare?
Report 49505 on a single line with modifier 50 and 1 unit. Chapter 12 section 40.7 says this is the Medicare rule even though CPT guidance uses two lines, and the bilateral indicator of 1 pays up to 150 percent. Check each commercial plan for its own policy.
05Is a hernia repair billed with another abdominal operation?
Only if it is at a different site and medically reasonable and necessary. NCCI chapter VI, item 4, says a repair at the site of the incision for an open or laparoscopic abdominal procedure is not separately reportable, and an incidental repair is not reported either.



Hernia claims denying on mesh or bilateral lines?
We check modifier 50, the mesh line and the incision-site rule against the operative note before the claim is sent.