
CPT 45378: diagnostic colonoscopy, and how it differs from screening G0121 and G0105
45378 reports a diagnostic colonoscopy: the scope is passed through the colon and nothing is biopsied or removed. When a Medicare patient is being screened, the claim carries G0121 or G0105 instead, and that choice decides what the patient owes.
 Written by Salman Saeed, CEO and Co-Founder · Reviewed by a Certified Medical Coder · Last reviewed October 2026
In short: 45378 is the base code of the colonoscopy family, with a 000-day global. A colonoscopy done to screen goes out under G0121 or G0105 on Medicare, and once a biopsy or removal happens the claim carries the code for that work with modifier PT.
What does CPT 45378 report?
45378 reports a colonoscopy with no treatment: the physician examines the colon and takes no specimen and removes nothing. CMS labels it "Diagnostic colonoscopy". Every colonoscopy code that adds a biopsy or removal names 45378 as its endoscopic base.
| Check | What the CMS files show |
|---|---|
| Payment status (RVU26D) | A, active |
| Global period | 000, a minor procedure or endoscopy |
| Multiple procedure indicator | 2; no endoscopic base code is listed for 45378 |
| Assistant at surgery indicator | 1, assistant may not be paid |
| MUE, effective October 1, 2026 | 1 per date of service, indicator 3, rationale "Nature of Service/Procedure" |
| ASC payment indicator, October 2026 | A2, with multiple procedure discounting |
Because 45378 is the base, it is not reported with a therapeutic colonoscopy code. Chapter VI of the NCCI Policy Manual says a diagnostic endoscopy code is not reported with a surgical endoscopy code. See 45385 for snare removal.
When is a colonoscopy billed as 45378 and when as G0121 or G0105?
Bill 45378 for a diagnostic colonoscopy and a screening code when a Medicare patient is screened. Chapter 18 of the Medicare Claims Processing Manual, section 60.1, says G0105 and G0121 are paid at rates consistent with 45378, so the fee matches. What differs is cost sharing: the manual states that the deductible and coinsurance apply to the diagnostic code.
| Code | Use | Medicare frequency (chapter 18, section 60.2) |
|---|---|---|
| G0121 | Screening, patient not at high risk | Once every 10 years: at least 119 months after the month of the last one |
| G0105 | Screening, patient at high risk | Once every 24 months: at least 23 months after the month of the last one |
| 45378 | Diagnostic colonoscopy | Not a screening code, so these intervals are not the test |
Section 60.3 lists high risk as, among others, a personal history of adenomatous polyps, a close relative with colorectal cancer or an adenomatous polyp, and inflammatory bowel disease. A screening colonoscopy that follows a positive stool-based test takes the KX modifier, and the frequency limits then do not apply.
What happens to the claim when a screening turns into a biopsy or removal?
The claim stops carrying G0121 or G0105. Chapter 18 says to bill the colonoscopy code for the biopsy or removal with modifier PT, which the October 2026 HCPCS file defines as a colorectal cancer screening test converted to a diagnostic test or other procedure. 45378 is not that replacement, because it describes an exam with no biopsy or removal. The cost-sharing phase-down and the sedation and anesthesia split are in gastroenterology billing.
How do I bill moderate sedation given by the same physician?
Medicare generally allows the physician doing the colonoscopy to report moderate sedation separately. Chapter II of the NCCI Policy Manual says so for codes 99151 to 99153. For a gastrointestinal endoscopy, HCPCS G0500 describes moderate sedation by that physician, with an independent trained observer, for the first 15 minutes at age 5 or older, and 99153 covers added time.
Chapter 18 adds the screening split. G0500 or 99153 with a screening colonoscopy carries modifier 33, which is the CPT preventive service modifier, and after conversion the sedation carries PT only. Anesthesia from a separate professional splits the same way: 00812 for a screening and 00811 with PT after conversion. See 00811.
How does 45378 appear on the claim, and what if the exam is not finished?
On the CMS-1500, 45378 goes in Item 24D with modifiers beside it, the place of service in Item 24B and the units in Item 24G. An ASC uses place of service 24 (Claims Processing Manual chapter 14, section 50). A hospital outpatient department bills the UB-04, and chapter 18, section 60.6, lists type of bill 12X, 13X, 22X, 23X and 85X for G0105 and G0121.
ASC addendum AA for October 2026 shows payment weight 9.0638 and a rate of $510.49 for 45378, with the same values for G0105 and G0121. For the diagnosis, ICD-10-CM guideline I.C.21.c.5 says a sign or symptom explains a diagnostic test, while a screening uses Z12.11, "Encounter for screening for malignant neoplasm of colon".
An interrupted exam still pays. A professional claim carries modifier 53 and chapter 18 pays one-half the value, using the file's own 45378-53 row. An ASC claim uses 73, paid at 50 percent, or 74, paid in full (chapter 14, section 40.4).
What fields hold a diagnostic colonoscopy?
A diagnostic colonoscopy is 45378 in Item 24D with 1 unit in Item 24G. When the exam began as a screening and turned diagnostic, the pointer in Item 24E and any modifier required by the payer must match the final findings. Item 24A holds the procedure date and Item 24B the place of service.
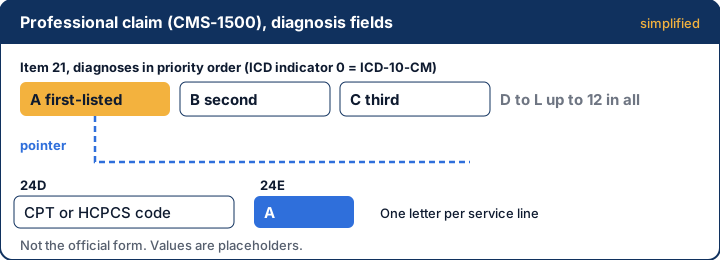
On a facility bill, the endoscopy revenue code is in FL 42, 45378 in FL 44, the date in FL 45 and 1 in FL 46. RVU26D gives 45378 status A and global 000, and the MUE table allows 1 per date with indicator 3.

Example: A patient with rectal bleeding has the exam on 10/07. The line is 45378, pointer A (K62.5), 1 unit, $780.00. If the claim was sent as screening and the findings were diagnostic, the payer may deny the mismatch under CO-11.
Why is 45378 denied?
| Code | What X12 says | What usually causes it |
|---|---|---|
| CARC 119 | Benefit maximum for this time period or occurrence has been reached | A screening code inside its interval; chapter 18 names 119 for this |
| CARC 97 | The benefit is included in the payment for another service already adjudicated | 45378 reported beside a therapeutic colonoscopy code |
| CARC 96 with RARC M83 | Non-covered charge; not covered unless the patient is classified as at high risk | G0105 billed for a patient outside the high-risk list |
| CARC 4 | The procedure code is inconsistent with the modifier used | PT, 33 or KX on a line the payer does not expect it on |
Chapter 18, section 60.8, still names CARC 46 with M83. X12 shows CARC 46 ended on 10/16/2003 and points to 96. If these denials keep coming back, our denial management team can work them. See also ASC billing.
Related codes
- Physician Fee Schedule relative value files, RVU26D (October 2026) · CMS
- Medicare NCCI Medically Unlikely Edits, practitioner services table, effective 10-01-2026 · CMS
- ASC payment rates and addenda, October 2026 Addenda AA and DD1 · CMS
- 2026 NCCI Medicare Policy Manual, Chapter II: Anesthesia Services · CMS
- 2026 NCCI Medicare Policy Manual, Chapter VI: Digestive System · CMS
- Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners · CMS
- Medicare Claims Processing Manual, Chapter 14: Ambulatory Surgical Centers · CMS
- Medicare Claims Processing Manual, Chapter 18: Preventive and Screening Services · CMS
- Medicare Claims Processing Manual, Chapter 26: Completing and Processing Form CMS-1500 Data Set · CMS
- HCPCS quarterly update, October 2026 alpha-numeric file · CMS
- ICD-10-CM Official Guidelines for Coding and Reporting, FY 2027 · CMS and NCHS
- Claim Adjustment Reason Codes · X12
- Remittance Advice Remark Codes · X12
- Medicare Claims Processing Manual, Chapter 25: Completing and Processing the Form CMS-1450 Data Set · CMS
We check every rule, code and deadline against the official source. See our editorial policy.
Common questions
Straight answers from the team that does the work.
Ask a billing lead directly. A 20-minute call, Monday to Friday, 9am to 5pm Eastern.
01How do I bill a diagnostic colonoscopy?
Report 45378 on the CMS-1500 in Item 24D with 1 unit in Item 24G and the place of service in Item 24B, with a sign, symptom or history diagnosis. Add 53 if the exam was interrupted. If a biopsy or removal happens, bill that code instead and drop 45378.
02How do I bill moderate sedation by the same physician?
Medicare generally allows separate reporting by the physician doing the procedure. For a GI endoscopy that is HCPCS G0500 for the first 15 minutes at age 5 or older, with 99153 for added time. With a screening colonoscopy the sedation line carries 33, and after conversion it carries PT.
03Does 45378 pay the same as G0121?
On Medicare, the fee matches. Chapter 18, section 60.1, says G0105 and G0121 are paid at rates consistent with 45378, and the ASC rate is the same. The difference is the patient's share, because the deductible and coinsurance apply to the diagnostic code.
04Does Medicare pay for an incomplete colonoscopy?
Yes. A professional claim carries modifier 53 and Medicare pays one-half the value, using the separate 45378-53 row. An ASC claim carries 73, paid at 50 percent, or 74, paid in full. The medical record must document the incomplete procedure.



Screening colonoscopies turning into denials?
We check the screening or diagnostic code, PT, 33 and KX against the payer's rules before the claim goes out.