
CPT 36556: non-tunneled central venous catheter insertion
36556 reports a physician or other qualified practitioner placing a central line that goes through the skin into a large vein without being tunneled under the skin first. It is a zero-day global procedure, usually billed with one unit, and the chest film that checks the tip is already part of it.
 Written by Salman Saeed, CEO and Co-Founder · Reviewed by a Certified Medical Coder · Last reviewed October 2026
In short: 36556 is the non-tunneled central line code. The October 2026 fee schedule file gives it a 000 global and no assistant payment, and its MUE is 2 on a clinical basis. NCCI will not pay the confirming chest film or a flow-directed catheter code on top of it.
What does CPT 36556 report?
CPT 36556 reports insertion of a non-tunneled central venous catheter. The line enters through the skin and ends in a large central vein without a tunnel under the skin. CMS prints the label "Insert non-tunnel cv cath" for both 36556 and 36555, which divide by patient age in the CPT codebook; read the age wording there.
| Item | Value in RVU26D (October 2026) and the Q4 2026 MUE file |
|---|---|
| Payment status | A (active; paid separately under the fee schedule if covered) |
| Global period | 000, so only the day of the procedure is in the package |
| Multiple procedure and bilateral | Multiple procedure 0; bilateral 0 |
| Assistant, co-surgeon, team | Assistant 1 (statutory restriction, may not be paid); co-surgeon 0; team 0 |
| Work RVU and total | 1.71 work; total 2.32 facility and 7.12 non-facility |
| NCCI MUE | 2 per date, MAI 3 (clinical data), practitioner and outpatient hospital |
Chapter 26 of the Claims Processing Manual marks place of service 21, 22 and 23 as facility sites and 11 as non-facility, so the same line pays from a different column in a hospital than in an office.
Which central line code fits the catheter?
The catheter type and the patient decide the code, and the choice also sets the global. Non-tunneled lines are zero-day; tunneled lines have 10 days, which pulls related follow-up visits into the package.
| Code | CMS short label | Global | Work RVU |
|---|---|---|---|
| 36555 | Insert non-tunnel cv cath | 000 | 1.88 |
| 36556 | Insert non-tunnel cv cath | 000 | 1.71 |
| 36568 | Insj picc <5 yr w/o imaging | 000 | 2.06 |
| 36569 | Insj picc 5 yr+ w/o imaging | 000 | 1.85 |
| 36557 | Insert tunneled cv cath | 010 | 4.77 |
| 36580 | Replace cvad cath | 000 | 1.28 |
NCCI Policy Manual chapter V, item 31, covers a failed first attempt. If one type of catheter is not completed and another type is placed at the same encounter, only the completed procedure is reported.
What is already included in a central line?
NCCI treats these as part of placing the line, not as separate lines.
| Service | Rule | Where it is stated |
|---|---|---|
| Chest film to confirm the tip (71045, 71046) | Integral to the insertion; not reported separately | NCCI chapter V, item 36 |
| Flow-directed catheter 93503 | Not reported with 36555 or 36556 for a single catheter | NCCI chapter V, item 31 |
| Right heart, selective venous or pulmonary artery catheterization | Not reported with a central venous access code | NCCI chapter I |
| General fluoroscopy 76000 or 77002 | Not reported; 77001 is the code for fluoroscopic guidance of central venous access | NCCI chapter I |
Can 36556 be billed with a visit or critical care on the same day?
A visit on the same day is bundled unless it is a significant, separately identifiable service. RVU26D says evaluation and management on the day of a 000 procedure is generally not payable, and chapter 12 section 40.1 allows a same-day visit only for a significant, separately identifiable service. Use modifier 25 on the visit in that case. Modifier 57 does not apply, because chapter 12 section 40.2 says it is not used with minor surgeries.
Critical care is different. Chapter 12 section 30.6.12.1 adopts the CPT list of services bundled into critical care, which includes vascular access procedures, and leaves time on separately reportable procedures out of critical care time. The CPT codebook sets which access codes are on that list. The critical care billing page works the line placement case, and the 99291 and 99292 pages cover time.
How does 36556 appear on the claim?
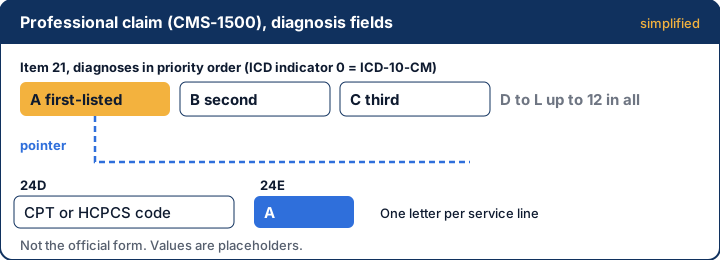
On the CMS-1500, Item 24B holds the place of service (21 for an inpatient stay, 23 for an emergency room), Item 24D holds 36556, Item 24E points to the diagnosis, and Item 24G holds 1. Hospital outpatient lines on the UB-04 use FL 44 and FL 46.
The MUE is 2 with an MAI of 3, which a contractor may bypass when the record shows the extra units were provided and medically necessary (NCCI chapter I). Assistant lines are the other trap: with assistant indicator 1, a line billed with 80, 81, 82 or AS is not payable.
How does a central line appear on the claim?
A non-tunneled central line is one line, 36556 in Item 24D with 1 unit in Item 24G and a pointer in Item 24E to the reason for access, such as shock or sepsis. What the code already includes, as set out above, gets no form line of its own.
On a hospital outpatient bill, the revenue code is in FL 42, 36556 in FL 44, the placement date in FL 45 and units in FL 46.

RVU26D lists 36556 as status A, global 000, and the MUE table allows 2 per date with indicator 3.
Example: On 10/13 a critical care patient has a line placed in the right internal jugular. The line is 36556, pointer A (A41.9), 1 unit, $390.00, with a procedure note giving the site and time. A second line on one date needs its own site and note.
Why do 36556 claims deny?
| CARC | What X12 says | What usually triggers it on a central line |
|---|---|---|
| 97 | The benefit for this service is included in the payment/allowance for another service/procedure that has already been adjudicated | Chest film, 93503 or general fluoroscopy billed with the line |
| 4 | The procedure code is inconsistent with the modifier used | Visit on the same day without 25 |
| 151 | Payment adjusted because the payer deems the information submitted does not support this many/frequency of services | Three or more units, or a second line with no note for it |
| 54 | Multiple physicians/assistants are not covered in this case | Assistant modifier on a code that bars assistants |
If these denials keep coming back, our denial management team can work them.
Related codes
- Physician Fee Schedule relative value files, RVU26D (October 2026) · CMS
- Medicare NCCI Medically Unlikely Edits, practitioner and outpatient hospital tables effective 10-01-2026 · CMS
- NCCI Policy Manual for Medicare Services, 2026 · CMS
- Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners · CMS
- Medicare Claims Processing Manual, Chapter 26: Completing and Processing Form CMS-1500 Data Set · CMS
- Medicare Claims Processing Manual, Chapter 25: Completing and Processing the Form CMS-1450 Data Set · CMS
- Claim Adjustment Reason Codes · X12
We check every rule, code and deadline against the official source. See our editorial policy.
Common questions
Straight answers from the team that does the work.
Ask a billing lead directly. A 20-minute call, Monday to Friday, 9am to 5pm Eastern.
01How do I bill central line placement in critical care?
Report 36556 on its own line with 1 unit and take the procedure minutes out of the critical care total. Chapter 12 section 30.6.12.1 says time on separately reportable procedures is not critical care time. The note should show when the line started and ended.
02Can I bill a chest X-ray to confirm the central line?
No. NCCI Policy Manual chapter V, item 36, says the film that confirms catheter position and rules out a pneumothorax is integral to the insertion, so 71045 and 71046 are not reported separately. A film ordered for another reason is a different case.
03Can 36556 be billed with 93503?
Not for a single catheter. NCCI chapter V, item 31, says 93503 is not reported with 36555, 36556, 36568 or 36569 for the insertion of one catheter. If one catheter type fails and another is placed, only the completed procedure is reported.
04How many units of 36556 can I bill?
The MUE is 2 per date with an adjudication indicator of 3. One unit is normal. A second unit needs documentation that two lines were each medically necessary, and chapter I of the NCCI manual lets a contractor bypass an indicator 3 edit when the record supports it.
05Can an assistant surgeon bill with 36556?
No. The RVU26D assistant-at-surgery indicator for 36556 is 1, which the file defines as a statutory payment restriction under which an assistant at surgery may not be paid. Co-surgeon and team surgery indicators are both 0, so modifiers 62 and 66 do not apply either.



Central line claims bundling away?
We check the chest film, the 93503 line and the critical care minutes against the procedure note before the claim goes out.